Lead malfunction revealed by an electric shock
Patient
Go to the casebook version optimized for the mobile experience
Male patient implanted with an Abbott Ellipse™ single-chamber defibrillator; consultation for syncope followed by electric shock
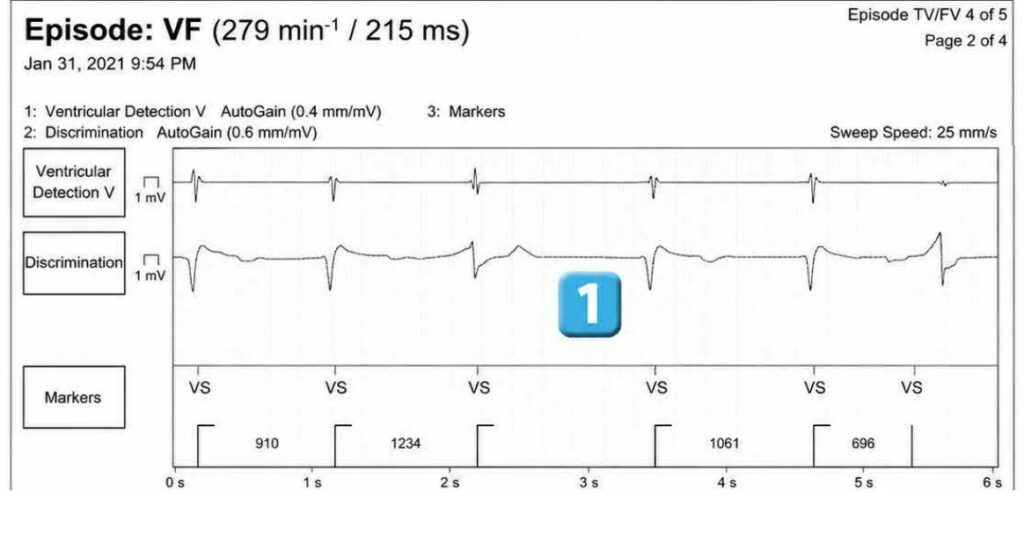
Trace
- sinus rhythm
- onset of ventricular arrhythmia
- After 20 cycles classified as F, diagnosis of VF and capacitor charging; the noise counter is reset to 0 provided that detection is correct on the discrimination channel ; 2 short cycles detected by the discrimination channel systematically reset the noise counter to 0 (<10 at the time of diagnosis)
- after a short charge (4 seconds), 15 joules electric shock
- probable reduction in arrhythmia but oversensing on the bipolar channel
- redetection of a VF episode and capacitor charging
- during charging, oversensing on the bipolar channel of non-physiological signals (short cycles, variable in amplitude and morphology); no oversensing on the discrimination channel
- at the end of charging, 30 joules electric shock; the SecureSense™ algorithm is not active in redetection after a first electric shock and therefore cannot inhibit therapies
- persistence of oversensing and redetection in the VF zone; new capacitor charge
- temporary shutdown of oversensing and diagnosis of sinus return after 3 cycles classified as VS
Comments
Episode of VF lasting 28 seconds with a first shock at 15 joules, a second at 30 joules, and a charge abandoned
Points to remember
- This trace shows an example of lead malfunction revealed after an electric shock delivered during a true episode of ventricular arrhythmia.
- An electric shock delivered to ventricular arrhythmia sometimes stretches a lead that is already already tense and weakened, and contributed to its definitive rupture; in this patient, stimulation impedances were strictly normal prior to this episode and no episodes of oversensing had been recorded in the memory; there were therefore no warning signs of lead dysfunction; the combination of the SecureSense™ algorithm, remote monitoring, and the responsiveness of the remote monitoring team significantly reduced the risk of inappropriate therapies in the event of lead breakage; however, as demonstrated by this example, this risk is not zero; in fact, in this case, no signs of lead breakage had been detected, and the inappropriate shock occurred immediately after the shock delivered for ventricular arrhythmia; once this inappropriate shock occurred, it was imperative to react quickly and deactivate the device as quickly as possible (magnet + deprogramming) in order to avoid the occurrence of additional inappropriate therapies.
- In this example, once the first shock has been delivered for an episode of ventricular arrhythmia, the diagnosis of oversensing is clear, with a discrepancy between false tachycardia on the bipolar lead and the absence of short cycles on the discrimination lead. Analysis by SecureSense™ would have inhibited therapies, but this algorithm is only active for the first therapy and cannot inhibit therapies once a first shock has been delivered.
Read more about related topics


