
Chapter 2 · Therapies · Case 7
ATP burst in the VF zone with acceleration
Patient and episode
Patient
- 83-year-old male with severe cardiomyopathy and permanent AF; implanted with an Incepta triple-chamber defibrillator
Summary
- Episode classified in the VF zone
- ATP in the VF zone and 31 Joule shock
The recording
Tap a number on the trace, or an entry in the list below
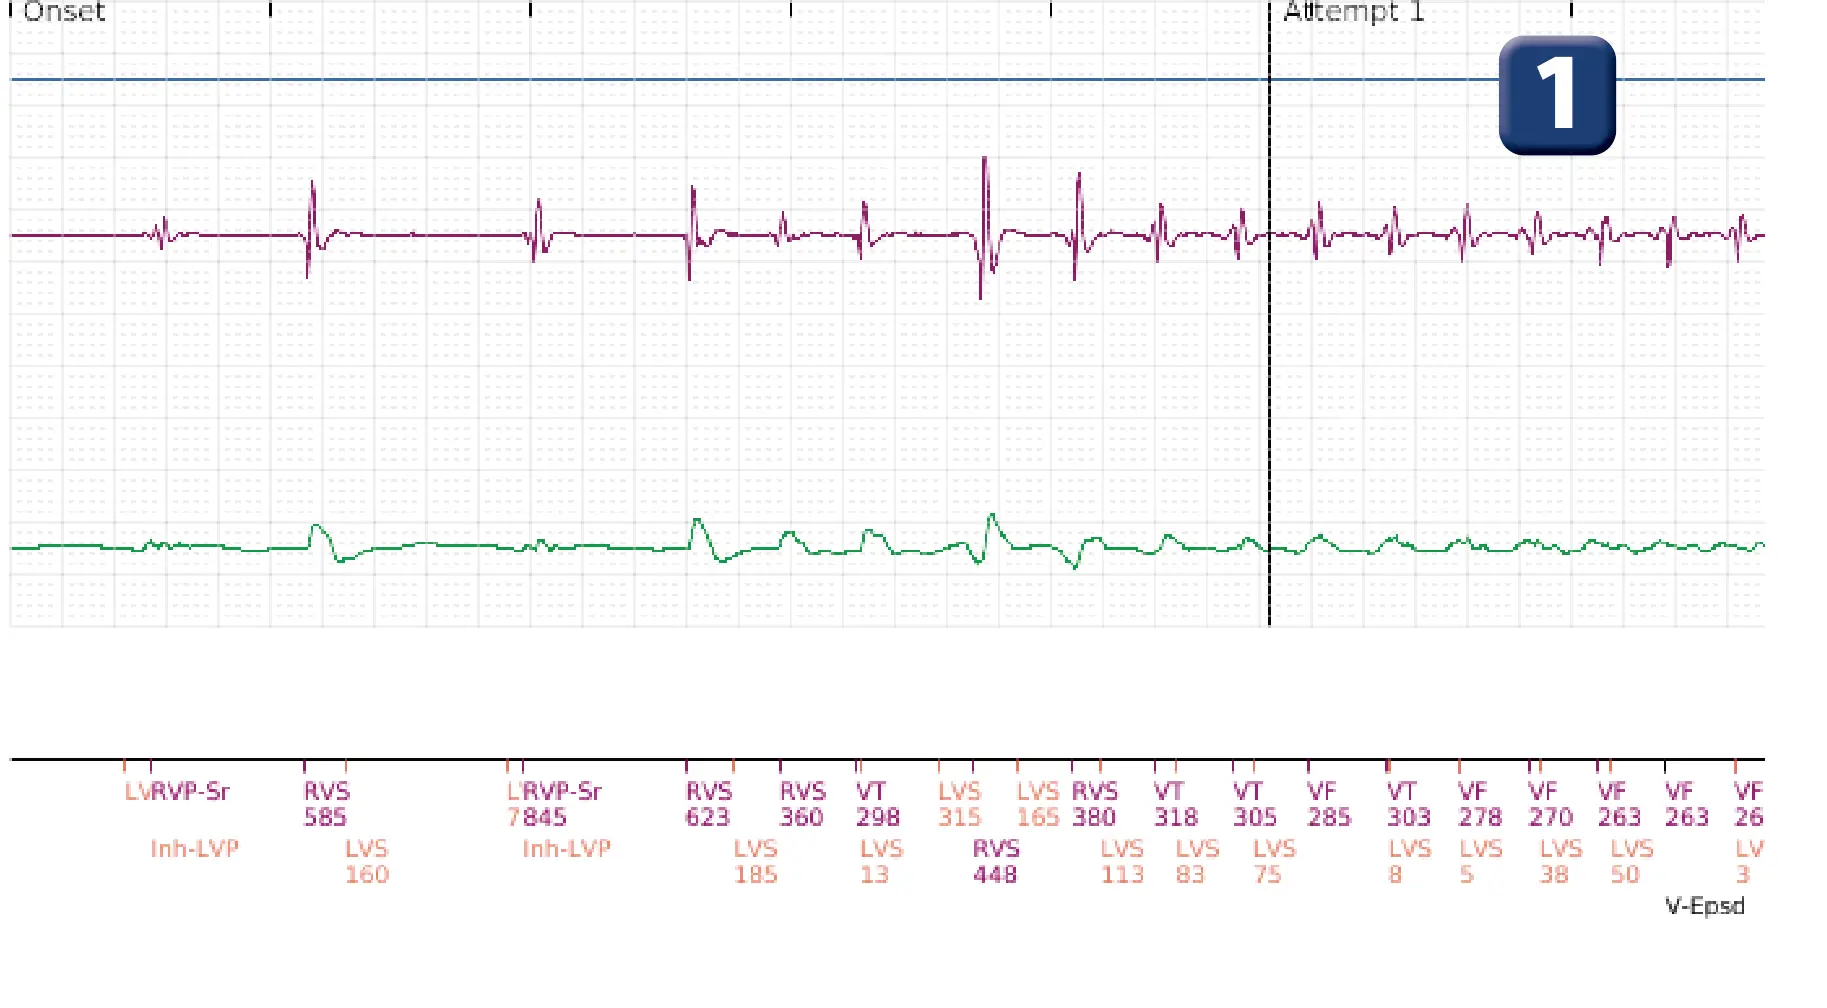
- Monomorphic VT detected in the VF zone
- Initial detection satisfied for VF zone (8 cycles out of 10 in FV zone); start of initial VF zone duration (1 second)
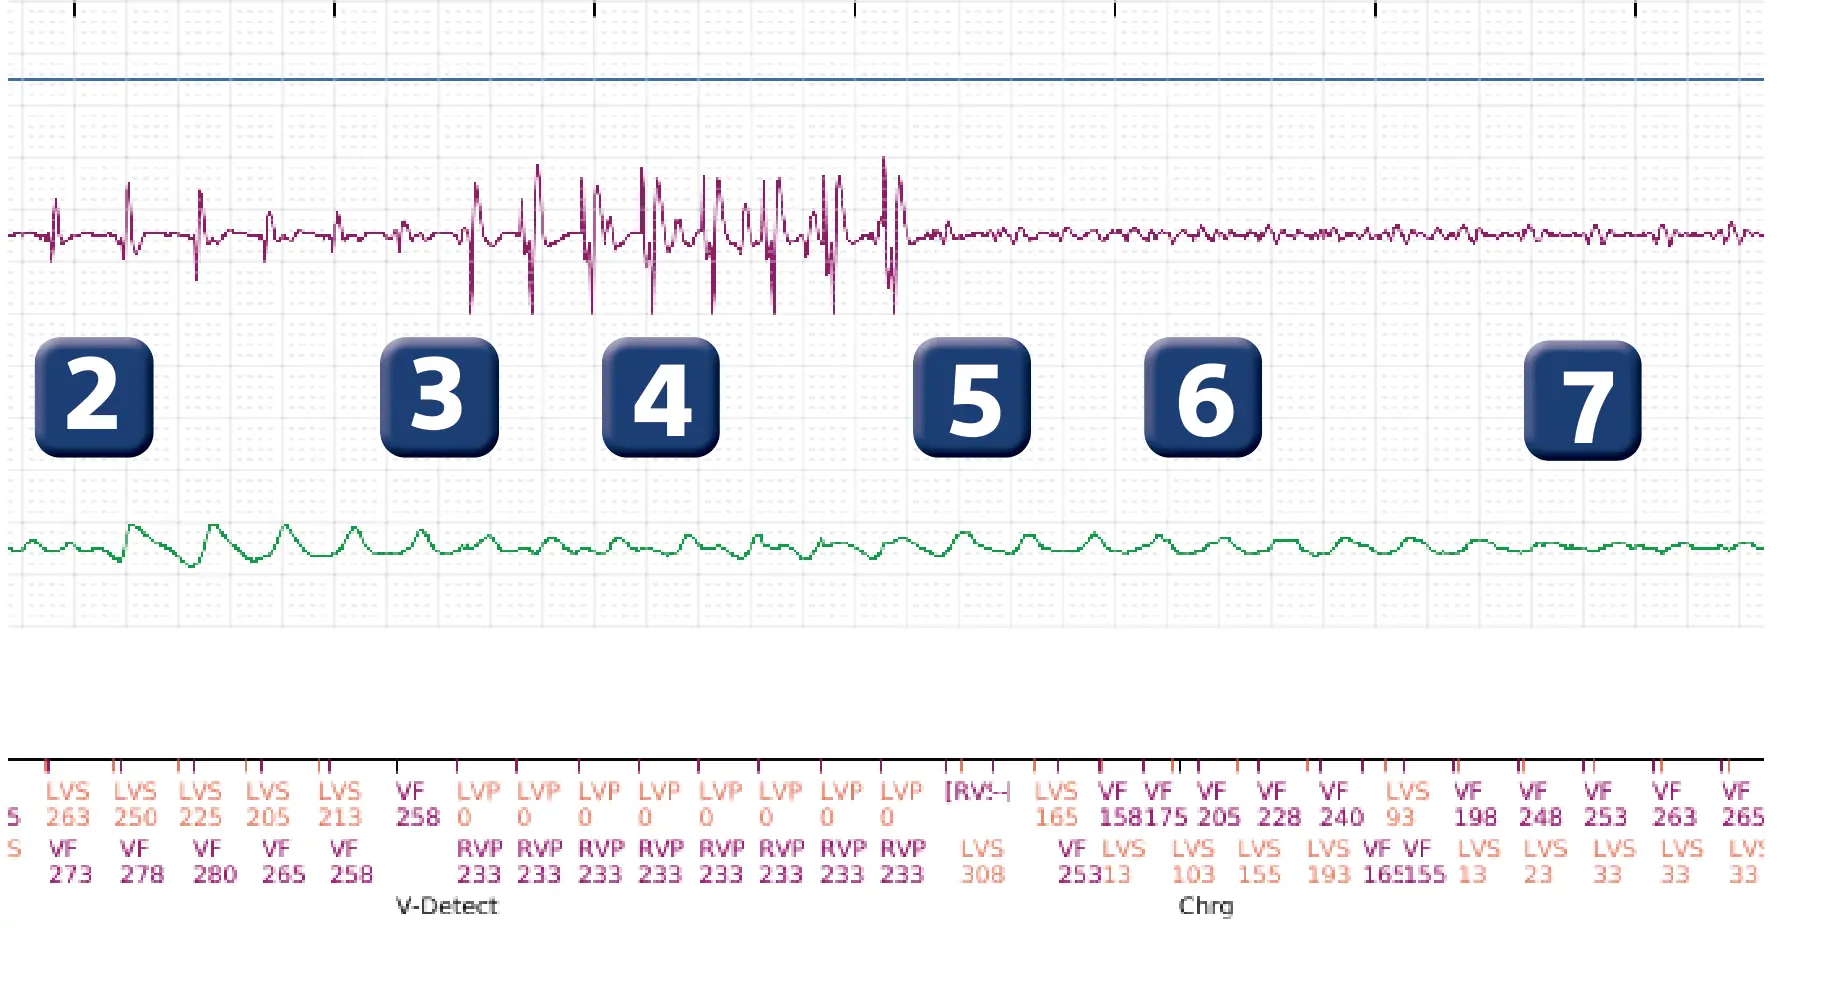
- Detection of a VF episode (V-Detect); ventricular rate measured over the 4 cycles preceding the V-Detect marker is below 250 beats/minute (226 bpm)
- ATP Quick Convert: burst of 8 stimuli at a fixed rate (identical coupling between the last sensed cycle and the first paced cycle, then between the different paced impulses).
- The first ventricular cycle is sensed in the refractory period following anti-tachycardia pacing (in square brackets); the second is not counted (--)
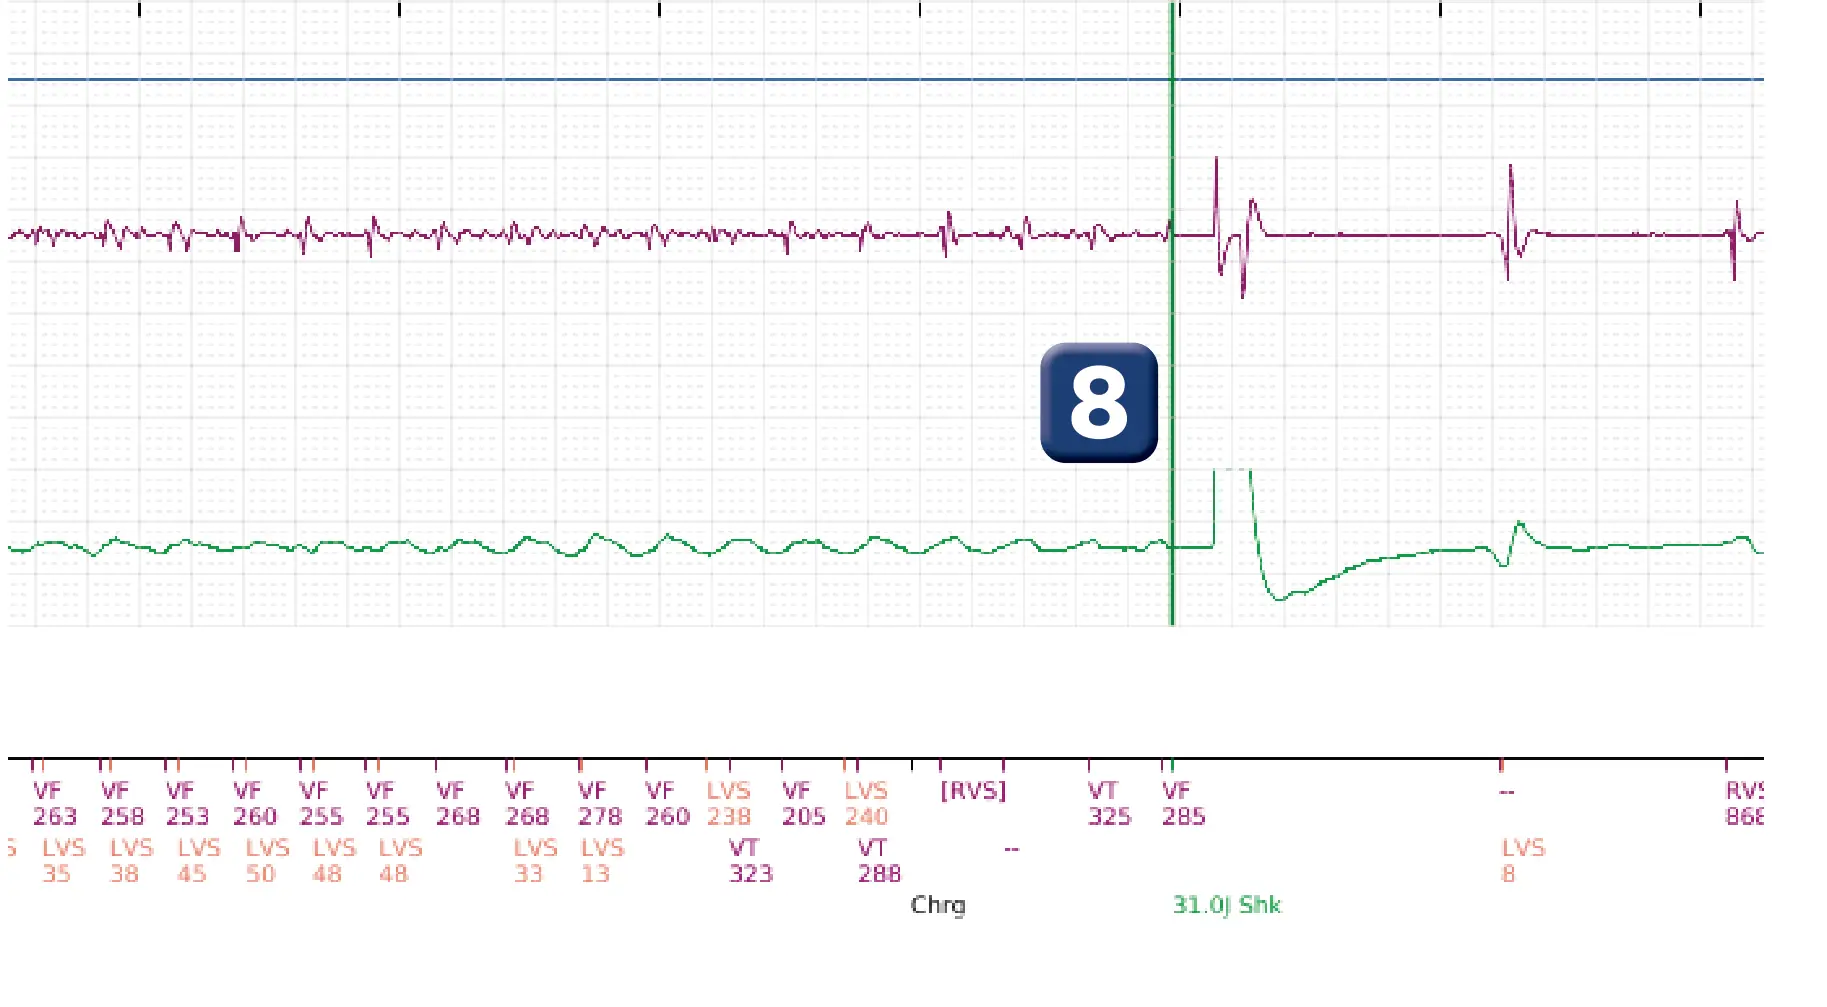
- The device analyzes the effectiveness of the pacing sequence: the first 2 cycles following the cycle that was no counted are considered fast (VF-VF); the 2 cycles/3 fast criterion is therefore met and capacitor charging begins (Chrg); when the burst has been ineffective, the start-of-charging marker appears on the trace 300 ms after charging has actually begun; charging begins on the second fast cycle, but the marker may not be visible until the third.
- Accelerated arrhythmia with rapid, low-voltage ventricular cycles
- End of charge, 500 ms diversion window; shock on second fast cycle
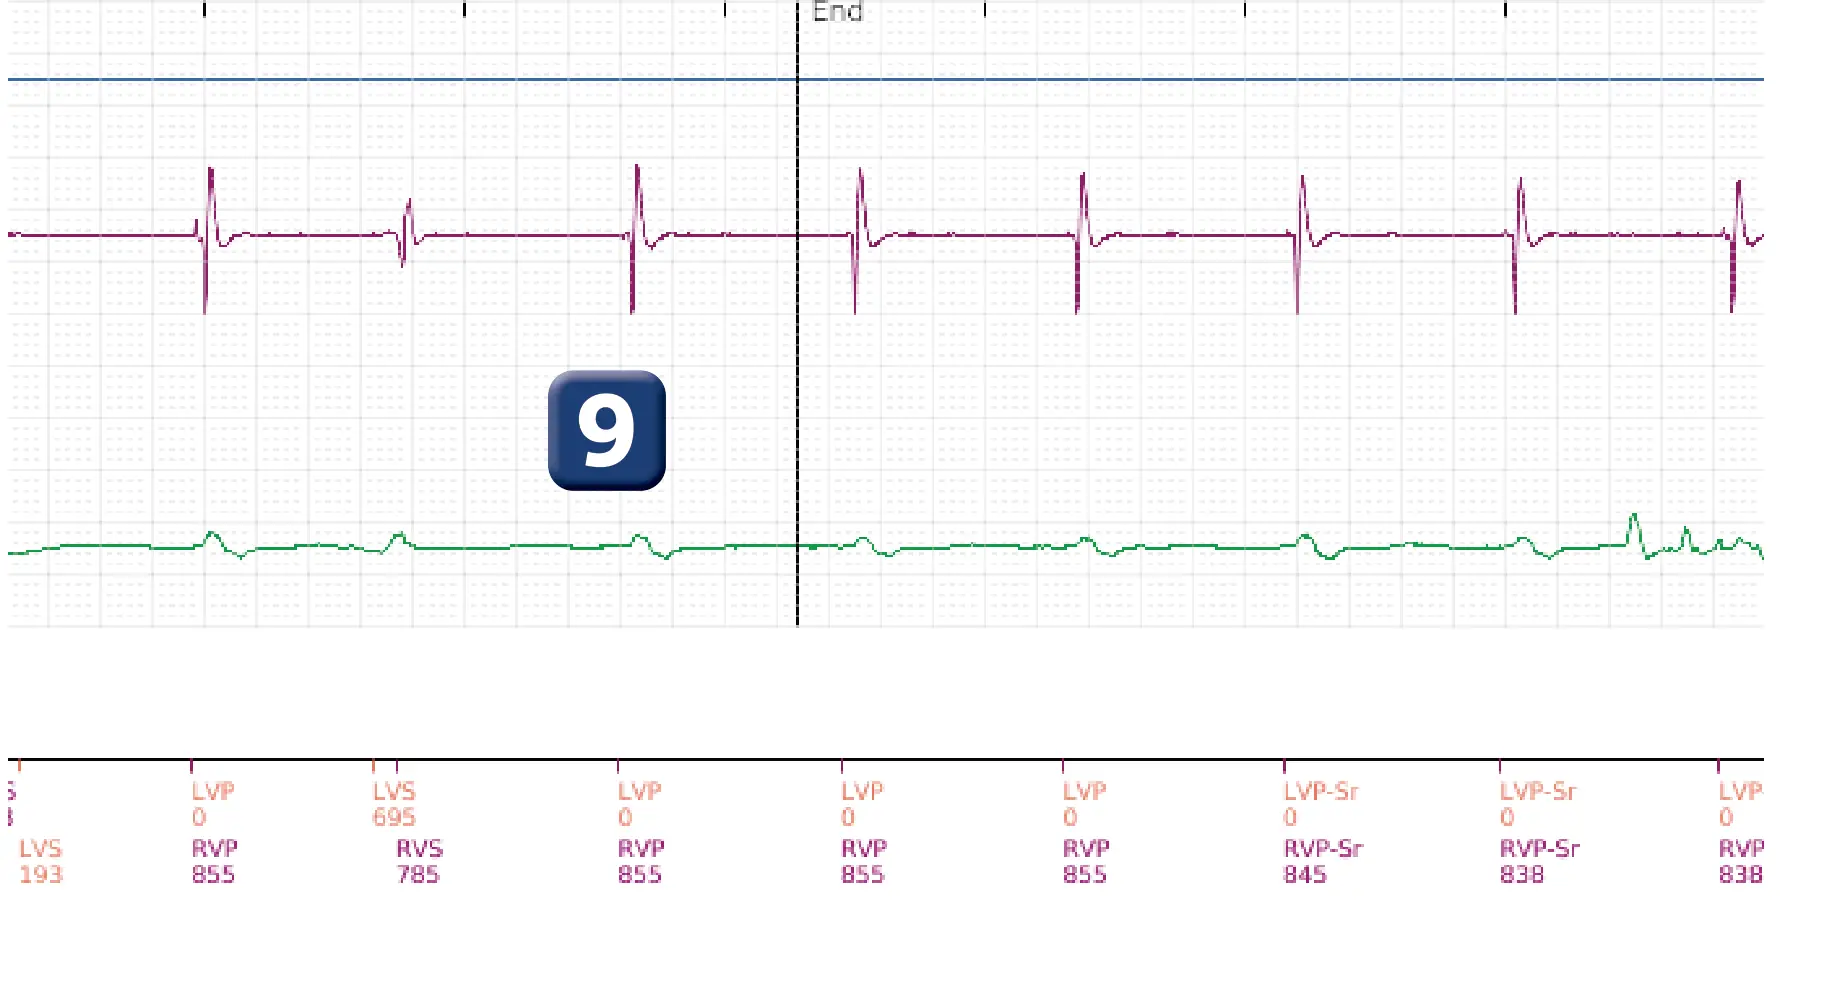
- Effective shock and arrhythmia termination
Points to remember
- ATP Quick Convert is the anti-tachycardia pacing sequence that can be delivered in the VF zone of a Boston Scientific defibrillator; it is ATP before charge.
- ATP before charging reduces energy consumption; once VF has been diagnosed, ATP is delivered; if VF is reconfirmed after ATP has occurred, capacitor charging begins; if arrhythmia terminates, charging is not initiated; this saves capacitor charging if ATP is effective; on the other hand, if ATP is ineffective, it delays shock delivery by 2 to 3 seconds
- This pacing sequence can only be delivered following initial detection in the VF zone, if the tachycardia sequence does not exceed 250 or 300 beats/minute (programmable on the latest platforms).
- The characteristics of this anti-tachycardia pacing sequence are not programmable: it is a burst of 8 stimuli with an 88% coupling interval
- Following this sequence, the device evaluates the effectiveness of the therapy; if at least 2 out of 3 cycles are considered slow, charging is cancelled; conversely, if at least 2 out of 3 cycles are considered fast, charging of the capacitors begins.
- In this example, ATP is not only ineffective but also accelerates tachycardia; a real-life study carried out on Boston Scientific defibrillators showed that, while the effectiveness of a first-line shock for an episode of VF averaged 90%, this success rate fell when the shock was delivered after an anti-tachycardia pacing sequence; one explanation lies in the risk of acceleration, as in this example, from a monomorphic arrhythmia to a very rapid polymorphic arrhythmia, with an increased risk of an ineffective shock; if ineffectiveness or a pro-arrhythmic effect is observed, it is advisable to deprogram the anti-tachycardia pacing sequence

Practice out loud
Just describe the tracing. What do you think is going on? Describing the numbers can help.
00:00
0%
—
From Boston Scientific ICD — clinical cases by P. Bordachar, M. Strik, A. Thiyagarajah, S. Ploux. Published by Cardiocases. Every numbered marker on a recording is explained in the list beneath it; tap a marker on the trace or an entry in the list.
Order hardcopyon Amazon